
Tummy Tuck After Weight Loss: The Future of Abdominoplasty in the GLP-1 Era
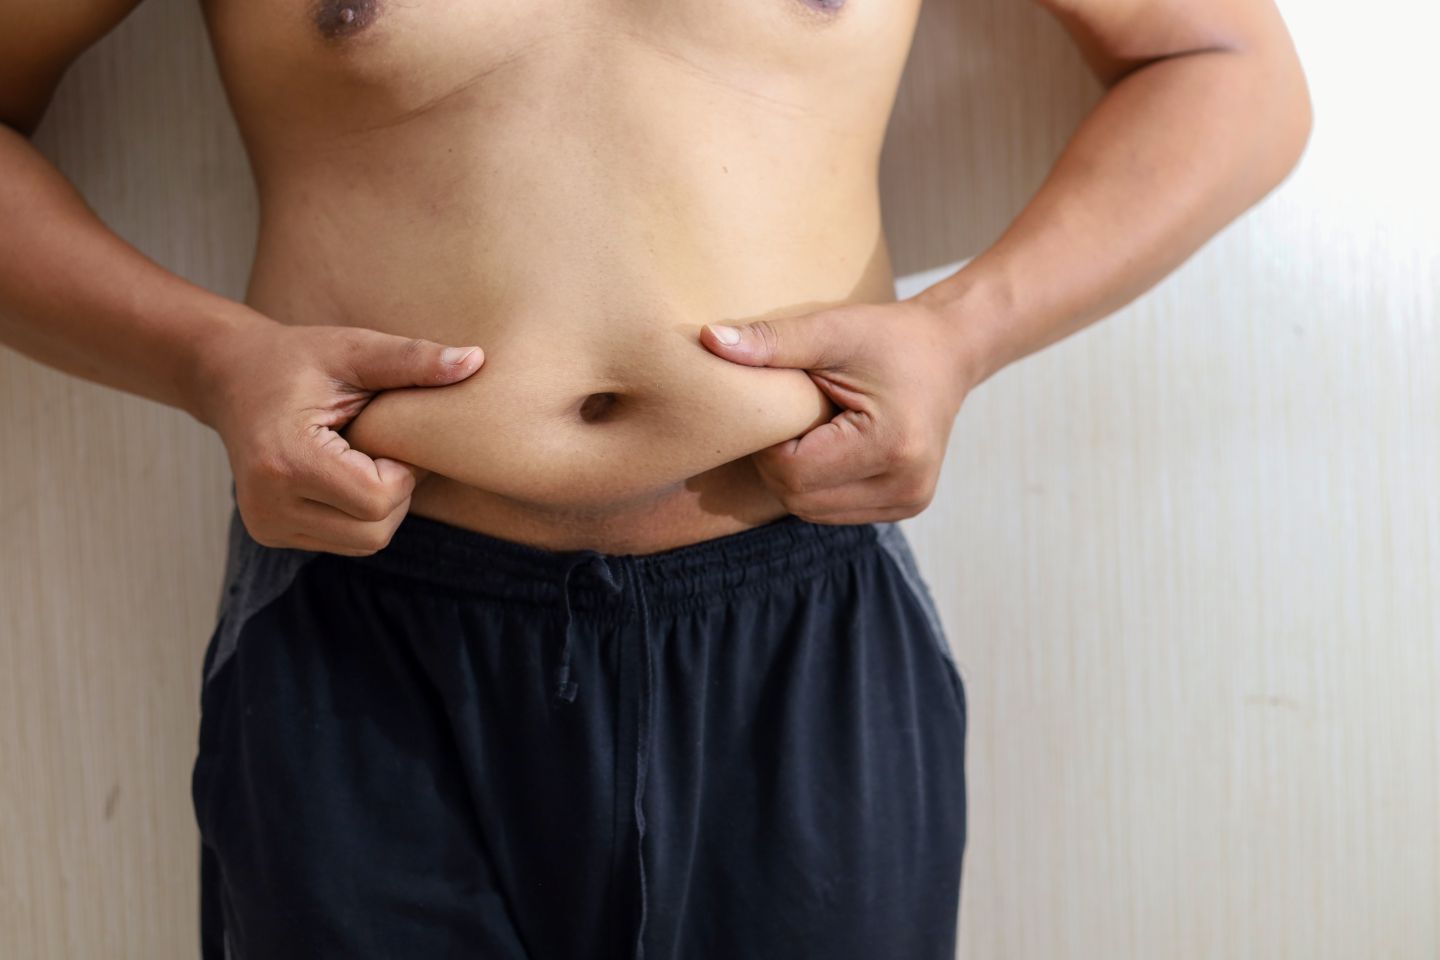
Every era of aesthetic surgery has a defining procedure, one that reflects what patients need most at that moment in history. In the age of GLP-1 weight-loss medications, that procedure is the abdominoplasty, more commonly known as the tummy tuck. Dr. Lisa DiFrancesco sees the tummy tuck becoming the signature operation of the weight-loss medication era and, increasingly, a functional restoration rather than a purely cosmetic one.
Why Weight-Loss Medications Cannot Replace a Tummy Tuck
The reason is simple and important. Weight-loss medications remove fat, but nothing they do removes skin. A patient who loses fifty, eighty, or one hundred pounds, whether through medication, bariatric surgery, or personal effort, is frequently left with an abdomen that no longer fits the body underneath it. After years of being stretched, the skin does not retract to match. What remains is loose tissue, a hanging apron of skin in more advanced cases, often a separation of the abdominal muscles beneath, and a mismatch between how far the patient has come and how the body looks.
This is not vanity. Excess abdominal skin causes rashes and infections in the skin folds, interferes with hygiene and clothing, limits physical activity, and undermines the confidence that motivated the weight loss in the first place. The tummy tuck is the operation that finishes what the medication started, and it is being reinvented right now to meet a wave of patients unlike any the field has served before.
The History of Abdominoplasty: From Removing an Apron to Restoring the Core
The earliest abdominal contouring operations, performed at the turn of the twentieth century, were essentially large excisions. Surgeons removed a heavy overhang of skin and fat, sometimes at the cost of the navel itself. These were crude solutions to an obvious problem.
The operation matured throughout the twentieth century, especially through the influential Brazilian school led by surgeons such as Ivo Pitanguy. This school refined the aesthetics of the tummy tuck by preserving and repositioning the umbilicus, improving the scar, and treating the abdomen as a contour to be sculpted rather than merely a defect to be removed. Two later advances went on to define the modern abdominoplasty.
Rectus Diastasis Repair
Surgeons recognized that pregnancy and weight change frequently separate the vertical abdominal muscles, a condition called rectus diastasis. Repairing this muscle separation restores the core, flattens the abdomen, and addresses a functional problem, not just an aesthetic one.
Lipoabdominoplasty
Around the turn of this century, surgeons began integrating liposuction with abdominoplasty, an approach advanced notably by Osvaldo Saldanha. Lipoabdominoplasty allows the flanks and upper abdomen to be sculpted while preserving the blood supply to the skin flap. This made tummy tuck results more refined and, when done correctly, safer.
Drain-Free Tummy Tuck Techniques
Along the way, techniques such as progressive tension sutures, championed by the Pollocks, reduced fluid collections and, in many surgeons’ hands, eliminated the need for drains. This improved the recovery experience considerably. The arc of this history runs from removing an apron of skin to restoring a core.
Modern Abdominoplasty: Body Contouring Plus Function
The contemporary abdominoplasty is best understood as an operation that does what no non-surgical treatment and no medication can do: it removes excess skin and repairs the abdominal muscle wall. Liposuction, energy-based devices, and weight-loss drugs each address fat. Only surgical excision addresses significant loose skin, and only surgical repair addresses muscle separation. Several realities define the current state of the art in tummy tuck surgery.
A Tummy Tuck Is Often Functional, Not Merely Cosmetic
Repairing rectus diastasis can improve core strength, relieve certain kinds of back pain, address associated hernias, and in some patients improve posture and even urinary symptoms. Removing a heavy panniculus resolves recurrent skin infections and rashes. The line between cosmetic and reconstructive surgery is genuinely blurry here, and that overlap is increasingly recognized.
Lipoabdominoplasty Is the Standard, Not the Exception
Combining skin excision, muscle repair, and liposuction contouring in one thoughtfully planned procedure produces a more sculpted, natural result than any single component could achieve alone.
Tummy Tuck Recovery Has Been Transformed
Drain-free techniques, enhanced-recovery protocols, long-acting local anesthesia, and multimodal pain control, which is often opioid-sparing, have made the recovery experience markedly more tolerable than the procedure’s reputation suggests.
Safety Planning Is Paramount
Abdominoplasty, particularly when combined with other procedures, carries a meaningful risk of blood clots, known as venous thromboembolism. Risk stratification, appropriate prophylaxis, and careful case selection are non-negotiable parts of responsible practice.
The Massive-Weight-Loss Abdomen May Need More
When weight loss is very large, a horizontal excision alone may not address vertical excess skin. In these cases, a more extensive pattern such as a fleur-de-lis abdominoplasty, which adds a vertical component, or a circumferential body lift may be required.
The Forces Reshaping Abdominoplasty
GLP-1 Medications: The Defining Force
No procedure is being reshaped by GLP-1 medications more directly than abdominoplasty, because the abdomen is where dramatic weight loss shows most visibly and most functionally. A new and enormous patient population is emerging: people who have achieved substantial, medically supported weight loss and now need their skin envelope addressed. Serving these patients well requires thinking beyond the operating room.
Weight stability comes first. Operating before weight has plateaued risks a result that loosens again, so most surgeons prefer a stable weight before finalizing a surgical plan.
Nutrition and protein are surgical variables. Adequate protein and micronutrients are essential for wound healing, and rapid or medication-driven weight loss can leave patients relatively depleted. Optimizing nutrition before surgery genuinely improves outcomes.
Muscle mass matters. Because GLP-1 therapy can reduce lean mass along with fat, preserving and rebuilding muscle through protein intake and resistance training supports both the aesthetic result and the functional recovery.
Medical optimization and perioperative planning, including individualized decisions about these medications around the time of anesthesia, should be coordinated among the surgical, prescribing, and anesthesia teams.
According to Dr. DiFrancesco, this is precisely where an integrated, physician-led approach produces the best results, one that treats weight loss, nutrition, hormonal health, and surgery as parts of a single plan rather than separate errands. The post-weight-loss abdomen is not just a surgical problem. It is a whole-patient problem.
Note: GLP-1 medications should be prescribed and managed by a qualified clinician, and perioperative decisions about them are individualized. Nothing here is medical advice.
Regenerative Medicine: Better Healing and Better Scars
The most conspicuous trade-off of a tummy tuck is its scar, and regenerative, healing-focused innovations aim to shrink that trade-off. Optimized wound healing through nutritional support, refined closure techniques, and evolving scar-management strategies improves the quality of the inevitable scar. Fat grafting can refine contour irregularities and improve transitions using tissue removed during the same operation. Regenerative and biologic wound therapies are also being explored to support healing, particularly in higher-risk patients after massive weight loss whose tissue quality is compromised, although many of these applications remain investigational.
The scar will not disappear soon, but the trend is toward healing that is faster, more reliable, and less visible.
Artificial Intelligence: Safer Patient Selection and Better Planning
Because abdominoplasty carries real medical risk and involves highly variable anatomy, it is fertile ground for AI-assisted decision-making. Risk prediction for complications such as fluid collections, wound-healing problems, and blood clots can support safer patient selection and individualized prophylaxis. 3D simulation and planning help align expectations and guide the choice between a standard, extended, or circumferential approach. Body-composition analysis can inform readiness for surgery, particularly for the post-weight-loss patient, where lean mass and nutrition matter.
The greatest near-term value of AI in tummy tuck surgery may be in safety and selection, matching the right operation to the right patient at the right time.
Longevity Medicine: The Abdomen as a Functional Core
Viewed through a longevity lens, the abdomen is not a cosmetic surface but the body’s functional core, central to strength, posture, and metabolic health. This reframes abdominoplasty as part of restoring function for the decades ahead. Core restoration through muscle repair supports strength, stability, and back health as patients age. Metabolic health is intertwined with abdominal fat and body composition, connecting body contouring to broader wellness. Sustained results depend on the patient’s ongoing metabolic and nutritional health, with surgery and lifestyle reinforcing one another.
In an integrated practice, the tummy tuck is not the end of a weight-loss journey but a milestone within a longer commitment to health.
The Future of the Tummy Tuck: Three Horizons
Near Term
Post-weight-loss abdominoplasty is expected to dominate practice, drain-free and enhanced-recovery techniques should become universal, and functional considerations such as muscle repair, hernias, and core strength will be increasingly emphasized. Energy-based skin tightening will serve milder cases, while surgical excision will remain essential for significant skin laxity.
Mid Term
Regenerative wound healing and scar-reduction strategies will meaningfully improve the operation’s chief trade-off, and AI-driven risk prediction will make patient selection safer and more precise. Integrated pre-surgical optimization of nutrition, muscle, and metabolic health will become standard for the post-weight-loss patient.
Long Term
As weight-loss medications reshape the population, abdominoplasty may be understood less as a cosmetic procedure and more as a restorative one: the surgical completion of a metabolic transformation, focused on function, health, and quality of life as much as appearance. Advances in skin regeneration may eventually reduce how much excision some patients require, though for significant laxity, thoughtful surgery is likely to remain necessary for the foreseeable future.
What This Means for Patients Considering a Tummy Tuck After Weight Loss
Medication cannot fix loose skin. For patients who have lost significant weight, surgery is currently the only way to address a redundant skin envelope and separated abdominal muscles.
Reaching a stable weight first is essential, since finalizing surgery before weight plateaus risks a result that loosens again. Nutrition is also part of surgery. Optimizing protein and overall nutrition before and after the procedure directly affects healing.
Patients should ask about function, not just flatness, because muscle repair and hernia assessment may matter for core health and not only for contour. Safety deserves serious attention as well, including an honest discussion of blood clot risk and recovery, especially when procedures are being combined.
Understanding Loose Skin, Liposuction, and Tummy Tuck Surgery
Loose Skin After Ozempic or Significant Weight Loss
Loose skin from Ozempic or other weight loss usually does not go away on its own when the loss is significant. Skin that has been stretched over time often loses the elasticity needed to retract, so it remains loose after weight loss. Non-surgical treatments help with mild laxity, but meaningful excess skin generally requires surgical removal.
Tummy Tuck vs. Liposuction
Liposuction removes fat but does not remove loose skin or repair separated muscles. A tummy tuck, or abdominoplasty, removes excess skin and repairs the abdominal muscle wall, and when combined as a lipoabdominoplasty, it also contours with liposuction. Patients with loose skin after weight loss typically need the tummy tuck, not liposuction alone.
When a Tummy Tuck Is Medically Necessary
A tummy tuck can be medically necessary. Removing a heavy overhang of skin resolves recurrent rashes and infections, and repairing separated abdominal muscles (rectus diastasis) can improve core strength, certain back pain, and associated hernias. Many cases combine functional and cosmetic benefits, blurring the traditional line between the two.
Timing a Tummy Tuck After Major Weight Loss
Most surgeons recommend waiting until weight has been stable for several months before surgery, since further loss can loosen the result. Nutritional optimization and, where relevant, coordination around weight-loss medications are also important before surgery. The timing is individualized for each patient.
Whether a Tummy Tuck Requires Drains
Tummy tucks do not always require drains. Many surgeons now use progressive tension sutures, which secure the tissue internally and often eliminate the need for drains while reducing fluid collections. Techniques vary, so patients should ask their surgeon about the specific approach and recovery protocol.
Risks of Abdominoplasty
Key risks of abdominoplasty include fluid collections (seroma), wound-healing problems, scarring, and, importantly, blood clots (venous thromboembolism), particularly when procedures are combined. Careful risk assessment, appropriate clot prevention, good nutrition, and proper patient selection significantly reduce these risks.
Medical Disclaimer
This article is for general educational purposes only and does not constitute medical advice, diagnosis, or treatment, nor does it create a physician-patient relationship. Aesthetic and surgical decisions must be individualized. Outcomes, risks, and candidacy vary from person to person. Some technologies discussed are emerging or investigational and may not be available, standardized, or approved in every region. Always consult a board-certified plastic surgeon and your own physicians before making any medical decision, and follow the guidance of your prescribing clinician regarding any medication, including GLP-1 therapies.
Clinical References
- Pitanguy I: refinements in abdominoplasty technique and aesthetics.
- Saldanha O: lipoabdominoplasty (integration of liposuction with abdominoplasty).
- Pollock H, Pollock T: progressive tension sutures and drain-free abdominoplasty.
- Literature on rectus diastasis repair and functional outcomes.
- Enhanced Recovery After Surgery (ERAS) protocols in body contouring.
- Venous thromboembolism risk assessment (e.g., Caprini) and prophylaxis in plastic surgery.
- American Society of Plastic Surgeons and bariatric/body-contouring guidance; annual procedural statistics.

Dr. Lisa DiFrancesco
Dr. Lisa DiFrancesco is a female board-certified plastic surgeon based in Atlanta, GA. Her specialties include, but are not limited to, body contouring after weight loss, skin tightening after weight loss, and abdominoplasty. She has won Castle Conolly Top Doctor for several years in a row, among other prestigious awards. Her expertise and experience makes her uniquely qualified to provide the utmost care and treatment for every patient.


